Starting Strength Training with Arthritis: What the Research Actually Says
Quick Answer: Strength training is recommended in major osteoarthritis guidelines and is one of the most effective non-drug interventions for joint pain and function. The rules for starting: begin with low load and higher reps, progress by roughly 10% at a time, use the 24-hour rule to judge whether a session was too much, and expect some discomfort during exercise to be acceptable. Two sessions a week is the effective minimum.
The instinct to protect a painful joint by not loading it is understandable and generally makes things worse over time. Muscle around a joint is load-sharing capacity, and it’s the thing you can actually build.


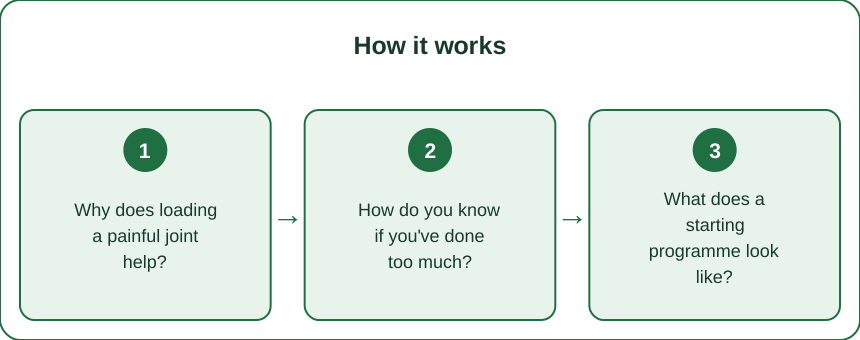
Why does loading a painful joint help?
Because most of the pain and function loss in osteoarthritis is not simply about cartilage wearing away.
Three mechanisms make strength work effective:
Muscle takes load off the joint. Stronger quadriceps and hip muscles absorb force that would otherwise pass through the knee. This is the most direct effect and the fastest to appear.
Movement nourishes cartilage. Joint cartilage has no blood supply and depends on load-and-release cycles to move fluid and nutrients through it. Sustained inactivity is genuinely bad for it.
Pain sensitivity reduces with graded exposure. Chronic joint pain involves a nervous system that has become more protective over time. Regular, tolerable loading gradually reduces that sensitivity - which is why people often report less pain doing more, once they’re past the first few weeks.
What the guidelines say: exercise, including strengthening, is a core recommended treatment for osteoarthritis in major clinical guidelines - typically listed alongside weight management and education, ahead of medication for many people.
The catch: it needs to be progressive and consistent. A month of gentle movement won’t do it, and neither will a fortnight of enthusiastic overloading followed by a flare and three weeks off.
How do you know if you’ve done too much?
The 24-hour rule, and it’s the most practical tool in this whole subject.
The rule: if your pain has returned to its normal baseline within 24 hours of a session, the session was appropriate. If it’s still elevated at 24 hours, reduce the load next time by about 25%.
What’s acceptable during exercise: discomfort up to roughly a 5 out of 10 is generally considered tolerable in exercise programmes for osteoarthritis, provided it settles afterward. Pain-free is not the requirement, and waiting for pain-free means never starting.
What’s not acceptable:
- Sharp, catching, or giving-way sensations
- Pain that increases through the session rather than staying level or easing
- Significant swelling afterward
- Pain that wakes you that night
The most common error in both directions: doing too much on the good days, which sets up a flare, then doing nothing during the flare. This boom-and-bust pattern is the single biggest obstacle to progress, and the fix is to do the same modest amount on good days and bad ones.
Write down what you did and how it felt at 24 hours. Three weeks of that data tells you your actual tolerance far better than any general guideline can.
What does a starting programme look like?
Two sessions a week, six exercises, roughly 25 minutes. Start lighter than feels necessary.
Weeks 1-2: establish tolerance. Bodyweight or very light band resistance, 2 sets of 10-12, slow tempo.
- Sit-to-stand from a chair - the single most functional lower body exercise there is
- Wall or counter push-up
- Seated or standing row with a band
- Standing hip abduction, holding a support
- Heel raises
- Seated knee extension, small range at first
Weeks 3-6: build. Same exercises, 3 sets, add resistance when 12 reps feels comfortable. Progress by roughly 10% at a time - a 10% jump is small enough that a flare is unlikely and large enough to drive adaptation.
Weeks 7-12: load properly. This is where the benefit accelerates. Move toward 8-12 reps with a resistance that makes the last two genuinely hard. Higher loads are appropriate and generally well tolerated once you’ve built up to them.
Add walking or cycling two or three times a week alongside. Cycling is often the best-tolerated cardio option for knee and hip arthritis because there’s no impact and the range is controlled.
Expect the first two to three weeks to feel worse before better. This is normal and is not the joint deteriorating - it’s unaccustomed muscle responding to unaccustomed work.

Myth vs Fact: Arthritis and Strength Training
Myth: Exercise wears the joint out faster. Fact: The opposite is better supported. Inactivity is associated with worse outcomes, and appropriate loading is a recommended treatment in clinical guidelines. Wear-and-tear is a poor model for what’s actually happening.
Myth: You should only do low-impact, light exercise. Fact: Low impact is sensible for cardio. But light resistance forever doesn’t build the strength that protects the joint. Progressive load is the point, and heavier loading is appropriate once you’ve built up to it.
Myth: Pain during exercise means damage. Fact: Moderate discomfort that settles within 24 hours is generally acceptable in osteoarthritis exercise programmes. Sharp pain, swelling, or pain lasting beyond a day is a different signal.
Myth: If your scan shows severe arthritis, exercise won’t help. Fact: Imaging findings correlate surprisingly weakly with symptoms and with response to exercise. People with significant changes on imaging frequently improve substantially with strength work.
Myth: You need a gym. Fact: Bands, a chair, and bodyweight cover the first two to three months entirely. Equipment becomes useful when you outgrow that, which is a good problem.
What about flares, cold weather, and bad weeks?
Plan for them in advance, because they’re guaranteed.
During a flare:
- Don’t stop entirely. Reduce load and range rather than dropping the session. Half the weight, half the reps, full attendance
- Keep moving the joint through comfortable range several times a day
- Return to your previous load gradually - typically over one to two weeks - rather than resuming where you left off
Cold and damp weather: many people report increased stiffness, and while the research on weather and arthritis pain is mixed, the practical response is straightforward. Warm up longer in autumn and winter - ten minutes rather than five - and consider exercising later in the day when you’re less stiff.
Morning stiffness that lasts under about 30 minutes is typical of osteoarthritis. Stiffness lasting significantly longer, particularly with swelling in multiple joints, is more suggestive of inflammatory arthritis and is worth raising with a doctor, because the management is different.
When to get professional input: a physiotherapist can build a programme around your specific joints and limitations, and in many health systems this is available without a referral. It’s the single most useful step if you’re unsure where to start, have multiple affected joints, or have had a joint replacement.
This is general information, not medical advice - check with your doctor or a physiotherapist before starting, especially if you have inflammatory arthritis, recent surgery, or other health conditions.
FAQ: Strength Training with Arthritis, Answered
How long before I notice a difference?
Most programmes show meaningful improvements in pain and function around 8-12 weeks. Some people notice changes in stiffness within three to four weeks. It’s not a fast intervention, which is why consistency matters more than intensity.
Should I take painkillers before exercising?
Discuss it with your doctor. Some people benefit from timing regular medication so exercise falls in a comfortable window; masking pain to push through more than you should is a different thing.
Is swimming enough on its own?
Excellent for movement and cardio, but it doesn’t provide the loading that builds muscle or bone. Best used alongside land-based strength work, not instead of it.
What if I’ve had a joint replacement?
Strength training is usually strongly encouraged afterward, but the specific restrictions depend on your surgery and surgeon. Get your programme from your surgical team or physiotherapist rather than a general article.
TL;DR:
- Strength training is a core recommended treatment for osteoarthritis, not a risk to the joint
- Use the 24-hour rule: back to baseline by tomorrow means the load was right
- Discomfort up to about 5/10 during exercise is generally acceptable; sharp pain and swelling aren’t
- Two sessions a week, six exercises, progress by roughly 10% at a time
- During a flare, reduce load and keep attending - never stop entirely
The joint isn’t a machine wearing out its parts. It’s a structure that shares load with muscle, and muscle is the part you can still build.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
